Ethics Part One: Data Collection and The Right to Effective Treatment

In the next few weeks I will be writing about ethics in the field of applied behavior analysis. This is the first part in a multi-part series.

Sometimes behavior analysts get a bad rap because we are so focused on the data. Somehow, there is a perception that writing down the numbers and graphing the information is “cold” or “unfeeling” towards the client. Over the course of my career, I’ve had more than one person say to me that I was more fun or more playful than they expected me to be as a behavior analyst. I’m not exactly sure where these misperceptions started, but today I want to get to the root of them.
As a BCBA, I am bound by the Professional and Ethical Compliance Code for Behavior Analysts. Within this code, it clearly states “Clients have a right to effective treatment.” This is something I take to heart every day in my work. And it’s the primary reason that I have my clipboard and am taking data. I want to ensure that the treatment I am introducing is actually effective. My data is what shows me when something is clearly not working, and allows me to be efficient with making changes the best benefit my client.
Clear, objective data allows me to be responsive to data and provide information in a responsible manner. Here are a few things to consider:
• When I graph data daily and look at that information, it’s very easy for me to see if a client’s performance has plateaued, is improving, or is actually getting worse. I can make adjustments based on the trend in the data.
• When all practitioners working with the client graph daily, I might (as the supervisor) see that the client is not performing as well with one practitioner. This might indicate that more training needs to occur. Or, I might see that one practitioner is getting far better results than the others. This might indicate that the practitioner is not recording data correctly or is doing something as part of the intervention that everyone should be doing.
• Data should be collected daily and the teaching programs should be clearly outlined. This way, if for some reason a practitioner abruptly stops working with the client or if the client moves, it is much easier for future practitioners to pick up where the last ones left off.
• Looking at data daily gives an idea of the individual client’s general trends in mastering new skills. For instance, last year I had a client who generally mastered new skills within one week, and his trend in the data was very consistent across all types of skills. So if we introduced a new program and he wasn’t mastering it for three weeks, it was an indication that we needed to re-evaluate what we were teaching or how we were teaching it. Being well-versed in your individual client’s learning patterns allows you to more clearly make individualized decisions!
We’d love to hear from you. What outcomes have you discovered in the relationship between being responsive to data and providing effective treatment for your clients?


WRITTEN BY SAM BLANCO, PhD, LBA, BCBA

Sam is an ABA provider for students ages 3-15 in NYC. Working in education for twelve years with students with Autism Spectrum Disorders and other developmental delays, Sam utilizes strategies for achieving a multitude of academic, behavior, and social goals. She is also an assistant professor in the ABA program at The Sage Colleges.

Discussing Concerns With Family Members

This month’s ASAT feature comes to us from Peggy Halliday, MEd, BCBA and David Celiberti, PhD, BCBA-D. To learn more about ASAT, please visit their website at www.asatonline.org. You can also sign up for ASAT’s free newsletter, Science in Autism Treatment, and like them on Facebook!


I am concerned that my two year old grandson may have signs of autism, but I am uncomfortable bringing this up with my son and daughter-in-law. Do you have any suggestions about how best to approach them?


It is natural to be unsure of how to share your concerns with your grandson’s parents. As is the case with many concerned family members, you may worry that such a discussion will not be well received or may cause some discomfort or tension in your relationship. If autism is a possibility, you would not want to delay screening and referral for possible evaluation and services because this may waste valuable time during which intervention can be most beneficial for your grandson. Even knowing that the best outcomes are associated with early diagnosis and intensive intervention, it still may be difficult to talk to your son and daughter-in-law if they have not expressed their concerns to you.

As a grandparent, you have already raised at least one child, so you probably have a good sense of what is typical in child development, and what is not. You may feel that your grandson is not making expected gains or may appear delayed in some areas such as communication or play relative to other children his age. Also, you may not have day to day contact so slower development of skills may be more apparent to you. This may create a sense of urgency in you that should be balanced with the need to support your son and daughter-in-law.

There are several important considerations. The way in which you approach your son and daughter-in-law will depend in large part on the quality of your pre-existing relationship and on the nature of how you communicate with one another. You may possess a relationship where difficult issues are frequently and easily discussed. On the other hand, this may not typify the type of relationship that you have. Regardless of your relationship, it is important that you bring this up from a place of love and concern, rather than judgment and blame. Many parents who have been carefully and respectfully approached by a relative later admit that they already had concerns of their own, and it was a relief to discuss them with someone else close to the child.

We would like to offer some concrete suggestions that may increase the likelihood that your discussion will be positive and constructive.

Planning Ahead:

  1. Take some time to think about what you want to share and how you want to frame your concerns. You might begin by commenting on the child’s strengths and praising the parents’ love and dedication to their child. It is important not to appear judgmental or focused only on the concerns.
  2. Plan your discussion ahead of time. Find a time and place when you will not be interrupted. It may be best when the child is with another caregiver.
  3. The role you take in the child’s life depends, of course, on geographic proximity, but be poised to offer concrete, practical help whenever possible. For example, you might offer to babysit siblings while parents pursue evaluation of the child, or offer a respite weekend of childcare so that your son and daughter-in-law might have time to discuss the situation without interruption. Whatever assistance you offer, the important thing is that your grandson’s parents perceive it to be helpful, so try and gauge their reactions carefully.

Having the Conversation:

  1. Try to keep the conversation free flowing. You may want to ask a few questions that will allow the parents to express their own concerns, if they have them (e.g., “I noticed that Billy became very upset when the phone rang. Has that happened before?” or “Does he seek you out when he is upset?”).
  2. Avoid labels and technical terms, which may trigger fear or upset from the parents. Focus instead on discussing milestones, which are observable indicators of a child’s development and accomplishments.
  3. In some cases, it may be beneficial to think about the discussion as a series of tiny conversations. This would be more appropriate if you have frequent contact with your son or daughter-in-law. It may then be helpful to share some observations that may provide a backdrop for later discussion (e.g., “Little Peter seems overwhelmed by noise levels.” or “I have noticed that he does not seem to know how to use words to get his needs met.). It may also be helpful to discuss observations surrounding worrisome or absent peer or sibling interaction.
  4. Emphasize the need to simply get any concerns checked out in order to “rule out” anything serious or to get some guidance and support in how to promote skill development. You might follow this up by mentioning that the earlier a potential problem is recognized and addressed, the easier it is to help the child.

Other Considerations:

  1. Most parents begin to become concerned that something may be wrong when their child is between the ages of 12 and 18 months. If the parents are beginning to realize a potential problem exists, you want to gently urge them not to delay a preliminary assessment and evaluation.
  2. You should never take for granted that developmental concerns will automatically be addressed during routine visits to the pediatrician. Refer parents to resources such as good websites and resources they can explore on their own (we emphasize the word “good” as there is a tremendous amount of misinformation about autism both in the media and on the Internet, particularly many false promises about autism treatment). The most helpful websites at this stage are typically the ones that discuss developmental milestones. Parents often know when to expect their infant and toddler to sit up or take their first steps, but they do not know when they should begin to babble with inflection, point to things they notice or want, imitate gestures, or show interest in another child.
  3. If the child is in a daycare, speak to his or her teachers and directors about the child’s progress. They should be keeping records on how the child is developing in different areas such as social interaction, verbalization, etc. They are also a good resource to use to help evaluate your child in a school setting.

The following websites include milestones checklists, booklets, and charts, and a wealth of other helpful information.

  • Association for Science in Autism Treatment (ASAT): On the ASAT website, you will find extensive information about the scientific support (or lack thereof) behind the full array of treatments proposed for autism, research reviews, articles and guidelines on how to make informed choices, and weigh evidence in selecting treatment options, a section of frequently asked questions such as the one you asked, information about upcoming conferences of interest, and links to helpful sites and other science-based organizations.
  • Centers for Disease Control and Prevention: The Act Early website contains an interactive and easy- to-use milestones checklist you can create and periodically update for children ages three months through five years, tips on sharing concerns with the child’s doctor, and free materials you can order, including fact sheets, resource kits, and growth charts.
  • First Signs: The First Signs website contains a variety of helpful resources related to recognizing the first signs of autism spectrum disorder, and the screening and referral process. There is a directory of local resources for at least eight states and that number is likely to increase over time.
  • American Academy of Pediatrics (AAP): The AAP website contains information for families, links to many other web sites, information about pediatrician surveillance and screening, and early intervention. This site contains great tools for pediatricians, as well as parents.
  • Autism Speaks: The Autism Speaks website includes an Autism Spectrum Disorder Video Glossary of clips designed to help parents and professionals learn more about the early ‘red flags’ of autism, information about how autism is diagnosed, and a resource library. They also offer a free 100 Day Kit designed to help families of newly diagnosed children make the most of the first 100 days following a diagnosis of autism.

About The Authors

Peggy Halliday, MEd, BCBA, is a Board Member of ASAT, and serves as the JCH Director of School Consultation at the Virginia Institute of Autism (VIA) in Charlottesville, Virginia, where she has been a practitioner since 1998. Peggy oversees trainings for parents and professionals and provides consultation to public school divisions throughout Virginia. She also oversees BCBA and BCaBA training experiences. In addition to serving as a presenter at state and national conferences, including the Organization for Autism Research (OAR), Commonwealth Autism Service (CAS), and Association for Behavior Analysis International (ABAI) Peggy was selected as an autism expert for the “how-to” website monkeysee.com. Peggy has been on the board of ASAT since 2010 and serves on the Public Relations Committee.

David Celiberti, PhD, BCBA-D, is the part time Executive Director of ASAT and Past-President, a role he served from 2006 and 2012. He is the Co-Editor of ASAT’s newsletter, Science in Autism Treatment. He received his PhD in clinical psychology from Rutgers University in 1993. Dr. Celiberti has served on a number of advisory boards and special interest groups in the field of autism, applied behavior analysis, and early childhood education, and been an active participant in local fundraising initiatives to support after school programming for economically disadvantaged children. He works in private practice and provides consultation to public and private schools and agencies in underserved areas. He has authored several articles in professional journals and presents frequently at regional, national, and international conferences. In prior positions, Dr. Celiberti taught courses related to applied behavior analysis (ABA) at both the undergraduate and graduate levels, supervised individuals pursuing BCBA certifications, and conducted research in the areas of ABA, family intervention, and autism.


Got Questions: Help for Socially Anxious Preschooler Who Has Autism

This piece originally appeared at Autism Speaks as part of their Got Questions? series.

My almost 3-year-old was recently diagnosed as having autism spectrum disorder. We struggle going places such as open gym or even the library because he doesn’t like other kids in his space. He does okay with adults, but other kids make him extremely anxious. How do I help him become more comfortable when other children are playing in the same area or with the same set of toys?

I commend you for seeking support for your son at this young age. Receiving a diagnosis of autism spectrum disorder can be challenging and confusing. Yet research shows that early intervention can help maximize cognitive, language and social development.

In my pre-doctoral work at UCLA and my post-doctoral training at Pediatric Minds Early Childhood Treatment Center, my colleagues and I have seen many forms of anxiety in children and teens who have autism. Like your son, many of them experience anxiety around other children, especially groups of children. Understanding the reasons for this anxiety can help select approaches that help.

For example, you mention that your son “does okay” with adults, but not other kids. This is very common. While adults tend to be more consistently friendly and accommodating, children can be very unpredictable. For instance, it’s not unusual for three-year-olds to grab toys from each other, cry, get very close to each other and just be loud! This can be particularly anxiety provoking for someone with autism.

In addition, many people with autism are hypersensitive to sensory input. As a result, public places such as open gyms or even a lively children’s library can be over-stimulating. The sights, sounds and smells can feel intense, uncomfortable and overwhelming. Understandably, this can lead a child to avoid these environments and become upset in the midst of them.

I strongly encourage you to work with your son’s therapists to develop a personalized intervention plan. Children with autism who are under age 3 can qualify for such services through their state’s Early Intervention program. After age 3, these services can be accessed as part of an Individualized Education Plan (IEP) through your school district.

Also see “Access autism services,” for more information on early intervention and individualized education services.
Fortunately, many programs are available to help young children with the type of social anxiety you describe. These include play-based forms of Applied Behavioral Analysis, occupational therapy that includes sensory integration, communication-focused intervention, social skills play groups and other options. Many children do best with a multidisciplinary approach that combines two or more of these methods with close collaboration among the care providers.

Also see, “Autism therapies and supports,” in the “What is autism?” section of this website. While every child has different needs, here are some strategies you can try – ideally in collaboration with your son’s therapists.

Practice. Are there specific social situations that tend to trigger your son’s anxiety? For instance, does he get upset when another child tries to take his hand or pull him into a game? Consider teaching him simple phrases he can use in these situations. For example, a simple “no.” You can also teach and practice toy sharing and turn taking at home. If your child enjoys play dough, for example, place just a few pieces on the table and take turns modeling each of the pieces, handing them back and forth. This can help him learn sharing and even waiting for gradually increasingly periods before getting what he wants. These skills can be difficult to learn. So start with brief periods of waiting and offer plenty of praise along the way. Providing this type of structured opportunities to practice social skills can encourage your son to use them in social settings.

Start slow. A room full of children may be too overwhelming for your child to use the new skills that he’s practiced with you at home. Consider hosting a playdate with one other child who is relatively calm and engaging. Sometimes, a slightly older child will understand how to be more accommodating.

In selecting where to have the playdate, consider your son’s comfort level. You might start at home or maybe a relatively quiet place at a nearby park.

Choose some relatively structured activities such as games or sharable toys that your child knows and likes. Keep the playdates relatively short to further the chances of success.

Bring the familiar. When entering a loud or anxiety producing environment, a comfort object may help provide a sense of security in an otherwise overwhelming environment. Consider allowing your son to bring a familiar toy, stuffed animal or book. Another possibility is a toy or game that actively engages his attention – and so directs his attention away from the hubbub around him.

Be patient. I encourage parents to appreciate that their child’s stage of development may not match what’s typical for his or her age. This is particularly true of social development in children on the autism spectrum. By focusing on small steps, you can foster your child’s confidence and decrease the likelihood of setbacks.

Remember, your child – like all children – is continually developing. You can support his social development – while decreasing anxiety around other children – by providing ample opportunities for success.


About The Author 

Dr. John Danial is a 2012 Autism Speaks Weatherstone predoctoral fellow. Dr. Danial’s fellowship supported his work with mentor Jeffrey Wood at the University of California, Los Angeles, developing and evaluating behavioral interventions that reduce anxiety in children, teens and adults with autism and low verbal skills. He is currently completing his post-doctoral placement at Pediatric Minds Early Childhood Center, working with families of children with developmental delays and social-emotional challenges.

NAVIGATING SESAME PLACE WITH A CHILD WITH AUTISM

This week’s post originally appeared on INCLUDEnyc,

As a mom of a three-year-old with autism, sometimes I’m hesitant to visit places that are overcrowded with people. I always worry that my son Julian will become overwhelmed and have a meltdown. Recently, his daycare took him on a trip to Sesame Place, and despite my worries, I decided to attend. I also invited a friend who has a five-year-old son with autism named Brandon (who is one of Julian’s BFFs).

I created a social story for Julian and told him about all of the characters he would see when we went there. I let him know that we would be playing in the water, going to see Elmo, and that we were going to go on fast rides that went up and down. I spoke to him about Brandon coming with us and how we would be taking a bus. He was very excited and told me he was very happy; or, in his words, “Mommy, Juju happy” (he refers to himself in the third person and always calls himself by his nickname).

The morning of the trip it was a little shaky; we took a car to his school (he was not happy about this because Mommy had only mentioned a bus). When we got on the bus, he was upset and overwhelmed with all of the new changes in his routine. I won’t lie — I was feeling a little overwhelmed myself. It took about 15 minutes for him to calm down, but after that he watched the cars as they drove by and ate lots of snacks, watched parts of a movie that was playing, and climbed all over me. In the end, he didn’t scream and cry the whole time, he didn’t get sick, and best of all, we made it in one piece.

When we arrived at Sesame Place we went straight to the Welcome Center, which was right by the entry gates and, oddly enough, not packed. I told the woman at the desk that we were traveling with two amazing little boys with autism. We were asked basic information like our boys’ names, birthdates, heights and addresses and we were each given a plastic wrist band with the numbers 1-3 on it (each number had a tab that ripped off the band) for water rides. This wristband allowed us to enter the rides through “Abby’s Magic Queue” and skip the long lines 3 times (good for 4 people each time). We were also given a small card with the numbers 1-6, which allowed us to ride 6 dry rides (good for 4 people each ride). We also rented a double stroller for less than $20 which allowed us to stroll both boys and carry our bags easily.

First we did the water rides. We went on a raft/slide ride near the entrance about 4 times in a row. Lucky for us they didn’t ask for any of the tabs. Both boys had a hard time waiting their turn but equally loved the ride; the smiles on their faces were priceless. Next we did the lazy river (for this ride they took one of our tabs); we were able to do this one twice as well. There are some parts on the lazy river where you will get splashed or sprayed by water; we just used ourselves as shields to block them (none of the boys like water in their faces). By the time we finished the lazy river, it was time for lunch. We had chicken fingers and French fries (which only came out to about $30 with a souvenir cup and plate).

Next we went on the dry rides and did just about everything in the Elmo’s World section of the park. For the dry rides we went to the exit and handed our cards to the attendant. They crossed off one number from the card and we were allowed to board the ride first. We had lots of fun on the spinning cups and air balloons. Apparently Julian has a thing for rides that go high in the air (me, not so much; I am afraid of heights). We also went to take a picture with Abby and Elmo, and we were super lucky that there was no line at all.

When it was time to leave, we got to watch some of the parade and wave to some of our favorite characters. Julian was very upset that we had to go and started to cry. Brandon was able to help soothe him by taking his hand and telling him that he was going to be ok. Julian slept the whole ride back on the bus after having some snacks and water. At the end of the day, we actually had a great time despite the normal meltdowns and moments of overstimulation. I was so happy that he had gotten to experience Sesame Place just like any other kid would.

I wrote this blog to encourage other moms of children with disabilities to try and worry less about all the things that can go wrong when experiencing new things, and to take the risk and go for it. Inclusion is one of the most amazing things that places like Sesame Place offer, and best of all, there are supports in place to support our kids. Of course there are going to be bumps in the road, but it’s nothing different than the ones we face every day. Go out, try new things, and follow your child’s lead; the worst thing that can happen is a meltdown (we deal with these anyway). But the best thing that can happen is the making of incredible memories.


About The Author

Millicent Franco is the Program Intake Coordinator for INCLUDEnyc. Millie helps coordinate services for Spanish bilingual families through the help line. Prior to joining INCLUDEnyc, she was a Family Support Worker via Healthy Families New York where she provided families with child development information/activities in order to help create a community of informed parents raising secure children. She also brings previous experience as a Case Manager for Turning Point’s transitional housing program. She is the proud mother of an amazing little boy with Autism and wants to help break the stigma associated with having special needs.

Interdisciplinary Collaboration and ABA

This week, Dr. Val Demiri PhD, BCBA-D, LBA offers some helpful advice on how to improve collaboration between professionals from different disciplines.

As professionals, collaborating with others in your work environment is an essential skill that may have been historically overlooked as part of the specific training you received as a behavior analyst. Currently, becoming credentialed as a Board Certified Behavior Analyst (BCBA) does not entail any coursework requirement in collaboration, however collaboration is mentioned as part of the Behavior Analysis Certification Board (BACB) 4th Edition Task List under Section II, and The BACB Code of Ethics as follows:

TASK LIST Section II: Client-Centered Responsibilities
G-06: Provide behavior-analytic services in collaboration with others who support and/or provide services to one’s clients.

BACB CODE: 2.0 – Behavior Analysts responsibility to clients:
2.03 (b) When indicated and professionally appropriate, behavior analysts cooperate
with other professionals, in a manner that is consistent with the philosophical
assumptions and principles of behavior analysis, in order to effectively and
appropriately serve their clients.

BACB CODE: 7.0 Behavior Analysts’ Ethical Responsibility to Colleagues.
Behavior analysts work with colleagues within the profession of behavior analysis and
from other professions and must be aware of these ethical obligations in all situations.
(See also, 10.0 Behavior Analysts’ Ethical Responsibility to the BACB)

These current ethical codes and task lists must be adhered to by behavior analysts and should raise questions on how to obtain the skills required for collaboration. Because we are an evidence-based and empirically oriented field, we may often find ourselves in the midst of conflict when presented with non-behavioral and non-evidence based treatments to our clients that other professions may be using or want to use. How do we resolve the ethical dilemma in the best interest of our client?
One suggestion is to seek supervision and training in collaboration. Over the years, the need for training (both didactic and hands-on) on collaboration with other professions has increased. Perhaps perspective and understanding of other professions and their ideologies are good places to start so that we put ourselves in better positions to present our understanding of what will help our client. Let’s face it, behavior analysis can seem stuffy and arrogant, if not cold, to other professions who pride themselves in helping clients and building connections and who may have little understanding of our field.
The research on collaboration is beginning to emerge within our field (Kelly & Tincani, 2013; Broadhead, 2015) and we can certainly look to fields outside of ABA who have taken it upon themselves to educate their profession on what applied behavior analysis is and how to forge collaborations as well as find common ground between fields (Donaldson & Stahmer, 2014). Donaldson & Stahmer (2014) published an article explaining the philosophy and principles of ABA to the speech and language profession, while also emphasizing common ground, mutual objectives and understanding of ABA. Within our own field, some initial steps in understanding collaboration was undertaken by Kelly and Tincani (2013) who conducted a survey of behavior analysts regarding collaboration using the following definition:

“A component of consultation involving voluntary, interpersonal interactions comprising of two or more professionals engaging in communication modalities for the purposes of shared decision-making and problem solving toward a common goal and resulting in changes to tasks and solutions that would not have been achieved in isolation.”

Not surprisingly, the survey revealed that 67% of respondents reported no coursework with “collaboration” in the coursework title and most surveyed agreed that they would want more training in collaboration (Kelly & Tincani, 2013). Even more striking were findings suggesting that behavior analysts were not necessarily team players during the collaboration process as collaboration was reported to be uni-directional (Kelly and Tincani, 2013). Unfortunately, the lack of collaboration may subsequently create conditions in which interventions are less likely to be implemented, simply because other professionals involved in the care of the client were not part of the decision making for those interventions (Kelly & Tincani, 2013).
More so than ever before, researchers, clinicians and educators find themselves working in settings with diverse professional disciplines that are responsible for treating the same individual. Nowhere is this example made clearer for behavior analysts than the settings in which a host of related services from varying professions are provided to students as part of their Individualized Education Plan (IEP). Understanding the dilemmas that behavior analysts might be faced with in terms of evidence-based interventions that are empirically sound, Broadhead (2015) offered a decision-making model for determining whether or not the proposed non-behavioral treatment is worth addressing. Broadhead (2015) suggested that gaining skills in systematically evaluating whether or not you question a treatment (which runs the risk of eroding relationships) vs. not addressing clearly dangerous and unhelpful therapies that have been debunked, (e.g., facilitated communication) can serve as clear guidance and decision making strategies when faced with such ethical dilemmas.
Understanding collaboration and gaining the skills needed to collaborate across disciplines should be both a professional goal and a goal within our field. In that spirit, the following tips for collaboration are offered:
1) Get to know the profession of others you work with in your setting. Ask for and offer others basic readings about your field, philosophy, and profession.
2) Talk about your own training and how you learned the skills you have and ask questions about training that other professionals have received in their field and how they came to acquire their skill set.
3) Be honest about philosophical underpinnings of how you have been trained (e.g., behaviorism, applied behavior analysis).
4) Discuss common goals you have for your client and how you can collaborate.
5) If appropriate, ask for a demonstration of a strategy or intervention, so you can see for yourself what is being done and offer to show how you would implement interventions for the same goal and discuss the commonalities or differences in strategies.
6) Set regular collaboration meetings and have an agenda where concerns, successes and progress are discussed.
7) Agree on a plan of intervention as a team.
8) Offer help with your skills that are applicable across all fields–such as data collection strategies, graphing, operational definitions, measurement of behavior, skill acquisition and progress.
9) Create a collaboration goal with someone outside your field.
10) Stay open to learning from others without compromising your ethical obligations as a professional and seek supervision.


Board, B. A. C. (2014). Professional and ethical compliance code for behavior analysts.
Brodhead, M.T., (2015). Maintaining Professional Relationships in an Interdisciplinary Setting:
Strategies for Navigating Nonbehavioral Treament Recommendations for Individuals
with Autism. Behavior Analysis in Practice, 8: 70-78.
Donaldson, A., & Stahmer, A. C. (2014). Team Collaboration: The use of Behavior Principles for
serving students with ASD. Language, Speech, and Hearing Services in Schools 45: 261–
276
Kelly, A., & Tincani, M. (2013). Collaborative training and practice among applied behavior
analysts who support individuals with autism spectrum disorder. Education and Training
in Autism and Developmental Disabilities, 120-131.


About The Author

Dr. Demiri received her doctorate in Clinical and School Psychology from Hofstra University in 2004 and her Board Certification in Behavior Analysis (BCBA) from Rutgers University in 2005.  She currently serves as an adjunct professor at Endicott College in the Van Loan School of Graduate & Professional Studies and she is the district-wide behavior specialist at Hopewell Valley Regional School District in New Jersey.  Previously she served as the Assistant Director of Outreach Services at the Douglass Developmental Disabilities Center of Rutgers, The State University of New Jersey, where she spearheaded the Early Intervention Program.  Her professional interests include diagnostic assessments, language and social skills development in individuals with autism spectrum disorders as well as international dissemination of Applied Behavior Analysis.  She has presented on Applied Behavior Analysis and autism locally, nationally and internationally.  Val is the co-author of the book, Jumpstarting Communication Skills in Children with Autism: A Parent’s Guide to Applied Verbal Behavior: Woodbine House.

Ball Games, Bowling, and the Bachelorette: Getting Individuals with ASD Interested in New Activities

While many adults retain some nostalgia for the characters, games, and toys of their childhood, there is a natural tendency to develop new and changing interests through adolescence and adulthood. For example, a child who likes Sesame Street and juice boxes will probably outgrow those interests in favor of sports and theater, beer and wine. For those with autism, however, rigidity in interests and limited tolerance for new activities can result in a lack of age-appropriate leisure skills in adolescence and adulthood. Because leisure is seen as something “fun” and therefore often unimportant – or at least, not as important as language, social, and academic skills – parents and teachers may be reluctant to challenge children to develop new preferences and leisure activities. It’s perfectly understandable for caretakers to prioritize the efforts and energy put into teaching new skills towards those that are most functional, and to allow play and leisure to be more child-directed.
There are two critical concerns with a failure to develop age- and socially-appropriate leisure skills, however. One major problem is that anyone who doesn’t have something enjoyable to do when the demands of everyday life are lifted may wind up engaging in less than acceptable ways of keeping busy. What they may wind up doing instead is often classified as inappropriate attention-seeking behavior towards peers and staff members, or even destructive or self-injurious behavior. A functional assessment of the concerning behavior often points to the simple problem of boredom, and teaching and encouraging new leisure skills is the best solution.
The second big problem is that socially, the world that we live in is frankly intolerant of adults who exhibit interests in and preferences for activities that are considered childish. There are some acceptable versions of these interests for adults; for example, there are plenty of grown-ups who enjoy creating elaborate model train scenes and who have the financial resources to do so. The individual with autism who loves Thomas the Train may be successfully able to transition that interest into the grown-up version of train hobbies, but will probably be most socially accepted if Thomas is not part of that adult hobby.
So what should be done about the problem of age-, culturally-, or socially-inappropriate interests? Is it even possible to build a new interest in someone who is resistant to unfamiliar activities? The answer is yes. Here are some suggestions to guide the process.
1. It’s always easier to teach what TO DO rather than what NOT to do. Rather than attempting to eliminate or discourage inappropriate interests, put more effort into encouraging appropriate interests to replace the problematic ones.
2. Consistent, regular exposure to new activities is the best way to encourage interest in those activities. “Try it, you might like it,” should be the mantra. Where some people have a natural curiosity and desire to seek out new experiences, people with autism often actively avoid them, so such exposure has to be programmed and guided.
3. If the individual is really resistant to trying something new, consider pairing the new activity with a preferred activity or item. Maybe watching a few minutes of a baseball game on television would be more appealing if favorite snacks were available, or doing some paint-by-numbers would be more likely if a preferred staff member was also doing it.
4. If possible, start exposure and pairing EARLY. Although it’s definitely possible to foster new interests in adults with autism, it’s much easier to establish a pattern of trying new things in a younger child. I strongly advocate having exposure to new activities as a part of regular programming along with language, academics, and social skills training, from the earliest possible point. You want trying something new to be a strong skill set.
5. Don’t get discouraged, and don’t force interests that aren’t being enjoyed. This is a tricky balance. It can take several exposures to get someone to start to enjoy something new, so don’t give up too quickly, but at the same time, know when to say when. If a good effort has been made to try something but the person just doesn’t seek it out after several opportunities, move on to another interest.
6. Keep an eye out for new possibilities, and build on existing interests. If someone genuinely enjoys drawing with markers, he or she may be open to painting, sculpting, or photography. If someone enjoys photography, maybe scrapbooking is a natural extension. An individual who likes to eat may be really motivated to learn to cook, and to enjoy cooking as an activity.
7. Look for ways to generalize existing interests. For example, an individual who enjoys looking up facts online can learn to enjoy researching trips or other leisure activities. Someone who likes to build with Legos might like to learn to put together model car kits or refinish furniture.
Age-appropriate leisure skills are important for many reasons, not the least of which is so that people don’t get bored and engage in problematic behavior when they have nothing else to do. Most adults have something to look forward to when their work is done, and those with autism deserve the same. Children who develop the skill of learning to try and like new things will definitely be a step ahead in terms of having good reinforcers and pleasurable experiences to look forward to throughout their lives!


About The Author

Dana Reinecke is a doctoral level Board-Certified Behavior Analyst (BCBA-D) and a New York State Licensed Behavior Analyst (LBA).   Dana is an Assistant Professor and Department Chair of the Department of Special Education and Literacy at Long Island University Post.  Dana provides training and consultation to school districts, private schools, agencies, and families for individuals with disabilities.  She has presented original research and workshops on the treatment of autism and applications of ABA at regional, national, and international conferences.  She has published her research in peer-reviewed journals, written chapters in published books, and co-edited books on ABA and autism.  Current areas of research include use of technology to support students with and without disabilities, self-management training of college students with disabilities, and online teaching strategies for effective college and graduate education.  Dana is actively involved in the New York State Association for Behavior Analysis (NYSABA), and is currently serving as President (2017-2018).

Teaching Adaptive Skills

In this months’s ASAT feature, Diane Adreon, EdD answers a question about what to consider when helping a child gain independence. To learn more about ASAT, please visit their website at www.asatonline.org. You can also sign up for ASAT’s free newsletter, Science in Autism Treatment, and like them on Facebook!

This article was originally published in ASAT’s free quarterly newsletter.


We are older parents and often lay awake at night worrying about our daughter’s ability to function independently when we are no longer able to care for her ourselves. She is 17 years old and is becoming more and more independent. We have read the “Hidden Curriculum” and that resource has opened our eyes to subtle social skills that may be missing in her repertoire. Are there adaptive skills that my wife and I should be considering that are often overlooked?

Individuals with autism spectrum disorders (ASD) typically have an uneven profile of skills (Ehlers et al., 2007). Regardless of cognitive ability, individuals with ASD often have difficulty with independent living skills. In fact, in many cases, areas of strength can mask significant deficits in adaptive skills. Adaptive behaviors are a reflection of the way an individual applies his or her cognitive skills in actual life situations. Research has shown that individuals with ASD have significantly lower adaptive behavior functioning than their measured cognitive abilities (Klin et al., 2007; Lee & Park, 2007; Mazefsky, Williams, & Minshew, 2007; Myles et al., 2007). This suggests that, no matter the individual’s level of functioning, we need to focus on teaching adaptive skills.

When identifying what skills to teach, it is important to remember that goals should be individualized. Some questions to ask in identifying goals for your daughter include:

  • Is the skill a reasonable one to teach given her age and her opportunities to perform the skill?
  • Will she be transitioning to a new environment in the next few years? If so, what skills will she need to be successful in that environment?
  • If your daughter is currently in a program that can address daily living skills, can the goals be formalized making them a part of her IEP or IHP?

The Adaptive Behavior Assessment System- Second Edition (ABAS-II; Harrison & Oakland, 2003), Scales of Independent Behavior-Revised (SIB-R; Bruininks, Woodcock, Weatherman, & Hill, 1997), or the Vineland Adaptive Behavior Scales- Second Edition (VABS-II; Sparrow, Cicchetti, & Balla, 2005) are all adaptive behavior assessment instruments that can yield information helpful in identifying goals. Although the overall scores will provide a global picture of your daughter’s adaptive skills, going over the specific items on the protocol will provide substantially more useful input in the identification of goals.

The science of applied behavior analysis (ABA) provides numerous strategies to assist in teaching skills. Baseline data supply information on current skill levels and can help identify target behaviors. A task analysis assists in breaking down complex tasks into smaller components and behavior chaining procedures can help determine which steps to teach first. In addition, behavioral shaping procedures and carefully constructed prompting hierarchies can help ensure that we are teaching skills in the most efficient and effective manner. Moreover, identifying reinforcers and using data to determine schedules of reinforcement can address motivational issues. Finally, teaching strategies to address generalization challenges can increase the likelihood of the individual learning to perform the skills in a variety of situations.

Since the scope of skills associated with independence is quite broad, the remainder of this response will focus on some adaptive skills that are often overlooked. When such skills are taught to individuals with ASD, they can become more independent.

Teach safe and practical money skills. When making purchases out in the community, it is a good idea to not “show” others how much money you have. Therefore, consider teaching your daughter practical strategies such as getting her money out of her wallet ahead of time, counting her money in her wallet and taking out just the amount of money she needs for a purchase. You may also want to teach her to make purchases using a debit card and the protocol for withdrawing money at an ATM. This includes teaching her to maintain an appropriate amount of space between her and others in the ATM line, putting the money into her wallet before walking away from the ATM, and so forth. It cannot be overstated that practice is essential for learning any of these skills. Some ways you can create more opportunities for your daughter to practice these skills include establishing a bank account and giving her a check for her allowance; thereby creating a reason for her to learn how to make deposits and withdrawals from an ATM. You can also have her practice making deposits and withdrawals inside the bank with a teller.

Teach your daughter to use a calendar to track upcoming events. For most of us, the number of things we need to remember increases significantly when entering adulthood. In addition, some of what we may need to remember occurs only periodically, and outside of our daily routines, thus it can be much harder to rely on one’s memory in those instances. Depending on your daughter’s level of functioning, your primary goal might be having her check her schedule to see what is happening that day or to prepare her for upcoming events and activities. In other instances, you can work with her on marking a calendar with upcoming events or reminders (e.g., return library book at school, swimming at Jake’s – bring swimming suit) and reviewing them daily. Teach her to get in the habit of referring to the calendar for information. Individuals with ASD need practice to use visual resources.

Teach your daughter to create and use her own to do list. Remember, a to-do list can use any kind of visual or cue so that your daughter understands what to do. Individuals of all functioning levels can learn to follow a to-do list if it is written at the appropriate level (may use pictures instead of words) and they have been taught to refer to it and do each task independently. For some, you may want to start early in having them write or type their to do list and learn to refer to it and check things off when done. It is also a good idea to help them identify and build in preferred activities to reinforce “work before play.”

Teach your daughter to take medication independently. Most of us use visual cues or create a routine to remind us to take our medication, so work to establish similar ones for your daughter. If the medication regime is complicated, consider using a weekly pill box and organizing the medication on Sundays. Or perhaps you have a visual reminder present at the breakfast table that says, “Take medication.” In some instances, this might mean having the medication bottle or pill box on the breakfast table. Establish the routine of having your daughter take the medication right before breakfast (if the prescription allows) as this will decrease the likelihood that she will forget it. Once you have introduced this routine, decrease your verbal reminders to take the medication and direct her attention to the visual reminder. If she has a smart phone, you can also teach her how to set up a daily reminder to take the medication at specific times.

Hopefully these suggestions and examples of possible targets have provided you with a few additional ideas on ways to ensure your daughter continues to make progress towards greater independence. Assessment of her skills across a number of domains (home, community, health, safety, and work) as well as reviewing her individual goals and progress on a regular basis can ensure an ongoing conversation about priority adaptive skills to help her continue moving\ forward. It does take time and practice, but the pay-off is worth it in the long run.

References

Bruininks, R. Woodcock, R., Weatherman, R., & Hill, B. (1997). Scales of Independent behavior-Revised. Rolling Meadows, IL: Riverside Publishing.

Ehlers, S., Nyden, A., Gilllberg,C., Sandberg, A. D., Dahlgren, S., Hjelmquist, E., & Odén, A., Jr. (1997). Asperger Syndrome, autism, and attention disorders: A comparative study of the cognitive profiles of 120 children. Journal of Child Psychology and Psychiatry and Allied Disciplines, 38, 207-217.

Harrison, P. L., & Oakland, T. (2003). Adaptive Behavior Assessment Systems (2nd ed.). Minneapolis, MN: Pearson Assessment.

Klin, A., Saulnier, C. A., Sparrow, S. S., Cicchetti, D. V., Volkmar, F. R., & Lord, C. (2007). Social and communication abilities and disabilities in higher functioning individuals with autism spectrum disorders: The Vineland and the ADOS. Journal of Autism and Developmental Disorders, 37, 748-759.

Lee, H. J., & Park, H. R. (2007). An integrated literature review on the adaptive behavior of individuals with Asperger syndrome. Remedial and Special Education, 28, 132-139.

Mazefsky, C. A., Williams, D. L., & Minshew, N. J. (2008). Variability in adaptive behavior in autism: Evidence for the importance of family history. Journal of Abnormal Child Psychology, 36, 591-599.

Myles, B. S., Lee, H. J., Smith, S. M., Tien, K., Chou, Y., Swanson, T. C., & Hudson, J. (2007). A large scale study of the characteristics of Asperger syndrome. Education and Training in Developmental Disabilities, 42, 448-459.

Sparrow, S., Cicchetti, D. & Balla, D. (2005). Vineland Adaptive Behavior Scales (2nd ed.). Minneapolis, MN: Pearson Assessment.


About The Author

Dr. Adreon is the associate director of the University of Miami-Nova Southeastern University for Autism & Related Disabilities (UM-NSU CARD). She also has a private consulting practice specializing in high-functioning autism spectrum disorder (www.spectrumlifestrategies.com, Info@spectrumlifestrategies.com)



Carefully Consider the Meaning of Independence

In working with individuals with autism, my goal is always to help them move towards independence. Recently, I was speaking with a colleague about an intervention I had done in which a child independently began his bedtime routine (brushing teeth, changing into pajamas, etc.) when his VibraLite watch vibrated at 8PM. When the watch vibrates, he resets it for 8PM the next day. Her response was that she didn’t believe that was truly independent behavior, since he required the prompt of the watch vibration. Many of you reading may agree with my colleague, but I think we must consider independence today in the context of our own behavior.

In the evening, I set an alarm clock, and I only wake up in the morning when it buzzes. When I run out of milk, I’ll put an alert in my Reminders app on my phone. When a friend invites me to lunch, I immediately enter the date in my calendar. All of these are technically examples of prompts, but if I am managing the prompts, I would argue that I am in fact engaging in independent behavior.

When I think about independent behavior, I want the children I work with to one day be able to grocery shop, go to work, eat a meal with a sibling, and more without having another adult facilitate those interactions. I want them to remember the time a movie starts, recognize when clothing needs to be washed, and pay their bills on time without another adult reminding them.

So, that begs the question: what counts as independence? We live in a time in which means we have a plethora of tools at our fingertips that weren’t available even a few years ago. Here are a few things you might want to think about in terms of independence:

  • What are the individual’s peers doing? Is it common for their peers to use a technological tool such as an iPad in the behavior you’re targeting? If not what are they using? Would that be an option for your learner?
  • What do you use in your day? If I’m using a Reminders app to keep track of my grocery list, then there’s no reason an individual with autism shouldn’t be allowed to do the same!
  • What does the research say? Many of the technological tools we use haven’t been out for very long, so it’s only been in the past couple of years that the research base is starting to catch up in terms of appropriate use of tablets, smartphones, and the like. But there’s a lot of good research out there! Take a look at the suggested reading list at the end of this article (and don’t forget to look at the reference lists in those articles to find more research.)
  • What does the individual gravitate towards? I have some students who prefer paper and pencil, and others that enjoy using tablets. I’m going to select interventions and tools for independence based on the individual’s own preferences! This may mean you have to try a few things out before you find the best fit.

All in all, I think it’s essential that individuals with autism be held to the same standard as the neurotypical population, not a higher standard when it comes to teaching independence.


Suggested Readings:

de Joode, E., van Heugten, C., Verhey, F., & van Boxtel, M. (2010). Efficacy and usability of assistive technology for patients with cognitive deficits: A systematic review. Clinical rehabilitation, 24(8), 701-714.

Hill, D. A., Belcher, L., Brigman, H. E., Renner, S., & Stephens, B. (2013). The Apple iPad (TM) as an Innovative Employment Support for Young Adults with Autism Spectrum Disorder and Other Developmental Disabilities. Journal of Applied Rehabilitation Counseling, 44(1), 28.

Kagohara, D. M., Sigafoos, J., Achmadi, D., O’Reilly, M., & Lancioni, G. (2012). Teaching children with autism spectrum disorders to check the spelling of words. Research in Autism Spectrum Disorders, 6(1), 304-310.

Kagohara, D. M., van der Meer, L., Ramdoss, S., O’Reilly, M. F., Lancioni, G. E., Davis,
T. N., Rispoli, M., Lang, R., Marschik, P. B., Sutherland, D., Green, V. A., & Sigafoos, J. (2013). Using iPods® and iPads® in teaching programs for individuals with developmental disabilities: A systematic review. Research in Developmental Disabilities, 34(1), 147-156.

Mechling, L. C., Gast, D. L., & Seid, N. H. (2009). Using a personal digital assistant to increase independent task completion by students with autism spectrum disorder. Journal of Autism and Developmental Disorders, 39, 1420-1434.

Uphold, N. M., Douglas, K. H., & Loseke, D. L. (2014). Effects of using an iPod app to manage recreation tasks. Career Development and Transition for Exceptional Individuals, 39(2), 88-98.

Van Laarhoven, T., Johnson, J. W., Van Laarhoven-Myers, T., Grider, K. L., & Grider, K. M. (2009). The effectiveness of using a video iPod as a prompting device in employment settings. Journal of Behavioral Education, 18(2), 119-141.

Wehmeyer, M. L., Palmer, S. B., Shogren, K., Williams-Diehm, K., & Soukup, J. H. (2010). Establishing a causal relationship between intervention to promote self- determination and enhanced student self-determination. The Journal of Special Education, 46(4), 195-210.


WRITTEN BY SAM BLANCO, MSED, BCBA

Sam is an ABA provider for students ages 3-15 in NYC. Working in education for twelve years with students with Autism Spectrum Disorders and other developmental delays, Sam utilizes strategies for achieving a multitude of academic, behavior, and social goals. Sam is currently a PhD candidate in Applied Behavior Analysis at Endicott College. She is also an assistant professor in the ABA program at The Sage Colleges.

Prompt Fading For Parents

This week, Leanne Page M.Ed, BCBA, offers advice on how to avoid prompt dependence. 

This piece originally appeared on bsci21.org.


“Dear Behavior BFF, I am not a parent myself but am writing you about my nephew. My sister and brother in law are constantly telling him what to say. “Tell her thank you. Say good morning. Say I want to eat dinner now.” I rarely hear the kid saying anything other than the exact words he is told to say. Is this normal? It seems like a terrible idea to me.”

The principles of behavior analysis can be helpful to anyone, not just parents.  What you are describing here is a high level of prompting that is likely leading to prompt dependence. The boy’s parents are giving so many prompts that he is not responding independently.

Is this normal? With parents – who knows?! We each do our own thing. We almost always start something with the purest of intentions as I’m sure your sister and brother in law have here. They want to help their son to speak, help him to participate in social interactions, and help him to learn to be respectful. But maybe they are helping too much.

It’s likely time for some prompt fading. When teaching new skills, it is common to start with high levels of prompting to help the learner practice success and receive positive reinforcement. But we can’t stay there forever. We have to fade out those prompts.

Other situations where parents are likely to over-prompt and be ready for some prompt fading strategies: toileting schedules and your child never initiates, always giving choices and never letting your child come up with a request independently, doing things hand over hand, doing daily living activities for your child, etc.

Step back one step on your prompts. Still provide a prompt, but scale it back a bit. Find where you are on this list and go down one.

  1. Full physical – hand over hand. Doing things FOR your child.
  2. Partial physical – still doing some parts hand over hand, but letting the child do some independently.
  3. Full verbal – telling them what to say as given in the original question above.
  4. Partial verbal – give part of the response, not the whole thing.
  5. Gestural – give a gesture or a cue

*This is not an exhaustive prompt hierarchy. There is more detail within behavior analysis but will stop here as parents are the intended audience and may not need that level of technicality.

Some ideas to fade out the full verbal prompt are to give an indirect or partial verbal prompt. From the examples you gave, instead, you could say:

“What do you say?”

“Do you need something?”

“Good ……”

Prompting your child can be a good thing, a great thing, even a research based thing. But when all you do all day is prompt- maybe it’s time to take a step back. Don’t drop the prompts all together. We still want to be sure the child is successful in each situation so they can gain reinforcement and see an increase of the desired behaviors in these situations.

Step back one prompting level at a time. When your child is successful at that level, step back again. Fade out the prompts until he is able to respond independently and the constant telling him what to say is a distant memory!

We barely scratched the surface on prompts and prompt fading. Here are some good places to start learning more about it!

Alberto, P. A., & Troutman, A. C. (2012). Applied behavior analysis for teachers. Pearson Higher Ed.

Cooper, J. (2009). 0., Heron, TE, & Heward, WL (2007). Applied behavior analysis.

MacDuff, G. S., Krantz, P. J., & McClannahan, L. E. (2001). Prompts and prompt-fading strategies for people with autism. Making a difference: Behavioral intervention for autism, 37-50.


About The Author

Leanne Page, MEd, BCBA, is the author of Parenting with Science: Behavior Analysis Saves Mom’s Sanity. As a Behavior Analyst and a mom of two little girls, she wanted to share behavior analysis with a population who could really use it- parents!

Leanne’s writing can be found in Parenting with Science and Parenting with ABA as well as a few other sites. She is a monthly contributor to bSci21.com , guest host for the Dr. Kim Live show, and has contributed to other websites as well.

Leanne has worked with children with disabilities for over 10 years. She earned both her Bachelor’s and Master’s degrees from Texas A&M University.  She also completed ABA coursework through the University of North Texas before earning her BCBA certification in 2011. Leanne has worked as a special educator of both elementary and high school self-contained, inclusion, general education, and resource settings.

Leanne also has managed a center providing ABA services to children in 1:1 and small group settings. She has  extensive experience in school and teacher training, therapist training, parent training, and providing direct services to children and families in a center-based or in-home therapy setting.

Leanne is now located in Dallas, Texas and is available for: distance BCBA and BCaBA supervision, parent training, speaking opportunities, and consultation. She can be reached via Facebook or at Lpagebcba@gmail.com.


Using Contingency Contracts in the Classroom

As adults, we’re fairly accustomed to contracts for car loans, new employment, or updates to our smartphones. But contracts can also be beneficial in the classroom setting.
A contingency contract is defined as “a mutually agreed upon document between parties (e.g., parent and child) that specifies a contingent relationship between the completion of specified behavior(s) and access to specified reinforcer(s)” (Cooper, Heron, & Heward, 2007). There are several studies that indicate using a contingency classroom can be beneficial in the classroom setting.
Cantrell, Cantrell, Huddleston, & Wooldridge (1969) identified steps in creating contingency contracts:
(1) Interview the parent or guardian of the student. This allows you to work together to identify problem behaviors to be addressed, identify the contingencies currently maintaining these behaviors, determine the child’s current reinforcers, and establish what reinforcement or punishment procedures will be used.
(2) Use this information to create a clear, complete, and simple contract. The authors provide examples of how these contracts might look. You can vary the contract based upon the behaviors you are addressing with your student and the student’s ability to comprehend such contracts.
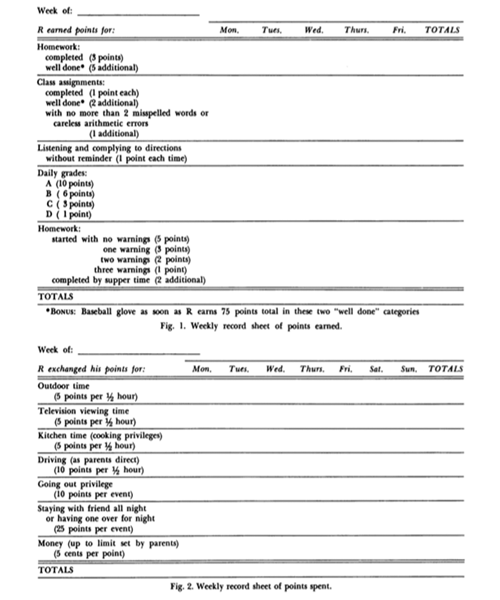
(3) Build data collection into the contract itself. You can see an example from the article below. For this example, it is clear how points are earned and how the child can utilize those points, and the contract itself is a record of both the points and the child’s behaviors.

BlogPic

There are clear benefits to utilizing such contingency contracting: building relationships across different environments in which the student lives and works, addressing one or more challenging behaviors simultaneously, and providing opportunities for students to come into contact with reinforcement. You can read the entire article here:

Cantrell, R. P., Cantrell, M. L., Huddleston, C. M., & Wooldridge, R. L. (1969). Contingency contracting with school problems. Journal of Applied Behavior Analysis, 2(3), 215-220.

And much more has been written about contingency contracting. If you’d like to learn more, we suggest taking a look at one or more of the following:

Bailey, J. S., Wolf, M. M., & Phillips, E. L. (1970). Home-based reinforcement and the modification of pre-delinquent’s classroom behavior. Journal of Applied Behavior Analysis, 3(3), 223-233.

Barth, R. (1979). Home-based reinforcement of school behavior: A review and analysis. Review of Educational Research, 49(3), 436-458.

Broughton, S. F., Barton, E. S., & Owen, P. R. (1981). Home based contingency systems for school problems. School Psychology Review, 10(1), 26-36.

Miller, D. L., & Kelley, M. L. (1991). Interventions for improving homework performance: A critical review. School Psychology Quarterly, 6(3), 174.


WRITTEN BY SAM BLANCO, MSED, BCBA

Sam is an ABA provider for students ages 3-15 in NYC. Working in education for twelve years with students with Autism Spectrum Disorders and other developmental delays, Sam utilizes strategies for achieving a multitude of academic, behavior, and social goals. Sam is currently a PhD candidate in Applied Behavior Analysis at Endicott College. She is also a lecturer in the ABA program at The Sage Colleges.